Shirdi Sai Hospital

Tag: shirdi sai hospital bangalore

  • PCOS and Ovarian Cysts: Are They the Same Condition?

    PCOS and Ovarian Cysts: Are They the Same Condition?

    By Shirdi Sai Hospital

    No. A separate ovarian cyst is not the same as the hormonal condition commonly known as PCOS. A cyst is a structural finding in or on an ovary. The syndrome involves a wider pattern of hormonal, reproductive and metabolic features.

    In 2026, PCOS was renamed polyendocrine metabolic ovarian syndrome, or PMOS. Patients may still see PCOS on reports and search for it online. We use both terms here to make the distinction clear: the syndrome is not simply a collection of ovarian cysts that needs removal.

    If your scan mentions cysts or polycystic ovaries, request a gynaecology review so the clinician can explain the finding.

    Why are the names so confusing?

    The older name, polycystic ovary syndrome, made many people assume that cysts were essential to the diagnosis.

    However, the small structures described in a polycystic ovarian appearance are follicles. A follicle is part of normal ovarian biology and contains a developing egg.

    That appearance is different from a separate cyst or mass needing its own assessment. It also does not, by itself, establish the syndrome.

    The newer PMOS name reflects the condition’s broader hormonal and metabolic nature. It is a name change for the condition, not a new diagnosis that every patient must start investigating from the beginning.

    What is an ovarian cyst?

    An ovarian cyst is a fluid-filled sac in or on an ovary. Some develop in relation to the menstrual cycle and may resolve without an operation.

    However, other types may persist or need a different assessment. For example, ultrasound can help describe the size, structure and features that guide follow-up.

    Therefore, a single cyst does not prove PMOS or PCOS. It also does not automatically mean cancer.

    The clinician needs to interpret the finding in the context of symptoms, age, menopausal status and the rest of the scan.

    Therefore, the word “cyst” alone is not enough to choose a treatment.

    What does the syndrome involve?

    The syndrome may involve irregular ovulation, menstrual changes and signs or laboratory findings of increased androgen activity. Metabolic health can also be relevant.

    Symptoms can include irregular or infrequent periods, acne, increased facial or body hair or scalp hair changes. However, not every patient has every feature.

    These symptoms also have other possible explanations. Assessment should consider relevant alternatives rather than diagnosing the syndrome from one symptom.

    The condition is not defined by pain from one isolated cyst. Removing a cyst is therefore not the same as treating the wider syndrome.

    Does ultrasound alone diagnose PCOS or PMOS?

    No. A scan is one possible part of the assessment. Therefore, the clinician reviews your history and relevant blood tests and checks for other causes.

    Some adults can meet the diagnostic criteria without needing an ultrasound finding of polycystic ovaries. Assessment in adolescents uses additional cautions, so clinicians must not apply adult scan rules casually to teenagers.

    A report saying “polycystic ovarian morphology” describes appearance. It does not automatically tell the clinician whether the full syndrome is present.

    Avoid using an online ultrasound image or a follicle count to diagnose yourself. The criteria need clinical interpretation.

    Can you have the syndrome without ovarian cysts?

    Yes. Clinicians can diagnose the syndrome without finding separate ovarian cysts.

    This is one reason the older name caused confusion. A person may have the syndrome even when the scan shows no separate cyst.

    However, the reverse is also true: someone with a cyst may not have the syndrome.

    If a previous diagnosis and a recent scan seem inconsistent, ask the clinician to explain which diagnostic findings supported the original assessment. Do not assume that a new scan has automatically confirmed or cancelled the diagnosis.

    Can both occur in the same person?

    Yes. A person with PMOS, previously called PCOS, can also develop an ovarian cyst.

    The cyst then needs assessment according to its own features. It should not be dismissed solely because a hormonal condition is already known.

    Equally, symptoms from a hormonal syndrome should not all be attributed to a cyst discovered incidentally.

    For example, irregular periods and a new episode of sudden severe one-sided pain may require different clinical questions. A known diagnosis does not remove the need to investigate an important change.

    Does either finding automatically mean infertility?

    No. Neither a report word nor a single ultrasound finding determines an individual’s fertility.

    The syndrome can affect ovulation, while a cyst’s relevance depends on its type and the wider reproductive situation. Many other factors influence the chance of pregnancy.

    If pregnancy is a goal, tell the gynaecologist. The assessment and treatment discussion should reflect that goal without promising a particular outcome.

    Do not assume that removing a cyst will correct all menstrual or ovulation problems. It is equally unhelpful to assume that a syndrome diagnosis makes pregnancy impossible.

    Why are the treatment plans different?

    Management of the syndrome addresses the features that matter to the patient, such as menstrual patterns, androgen-related symptoms, metabolic health or fertility goals.

    Management of an ovarian cyst may involve monitoring, additional investigation or surgery in selected circumstances.

    Therefore, these findings need different care plans. A medicine prescribed for a hormonal symptom is not a universal treatment for every ovarian mass.

    This article is intended to clarify the distinction, not to choose a drug or operation. The correct next step follows the clinical assessment.

    Do not start or stop hormonal treatment because a scan uses a different term from an older report.

    What should you bring to a consultation?

    Bring the actual ultrasound report, previous scans, menstrual history and relevant blood-test results. Include the names and dates of hormonal medicines or supplements you use.

    It can help to record:

    • How often periods occur and whether the pattern has changed.
    • Any acne, hair or other hormonal symptoms.
    • The location and timing of pelvic pain.
    • Whether the cyst is new or appeared on earlier scans.
    • Pregnancy plans or the possibility of pregnancy.
    • Previous ovarian surgery or important family history.

    Ask the clinician to separate three questions: what the scan shows, whether the syndrome is present and what requires treatment now.

    When should symptoms be checked?

    Arrange a gynaecology review for persistent menstrual changes, symptoms affecting daily life or uncertainty about a cyst report.

    Sudden severe pelvic pain, particularly with vomiting, needs urgent assessment. Fainting, severe weakness, fever, heavy bleeding or rapid deterioration also needs urgent care.

    If pregnancy is possible, mention it promptly. Do not assume that every pelvic symptom is explained by a previous PCOS or cyst diagnosis.

    Our pelvic-pain guide explains why symptom assessment can involve several possible causes.

    Getting the terminology clear

    A separate ovarian cyst, a polycystic ovarian appearance and the syndrome now called PMOS are related terms in ovarian health, but they are not interchangeable diagnoses.

    For a planned report review, contact Shirdi Sai Hospital on New BEL Road. Bring the scan and earlier results so the consultation can address the actual finding and your concerns.

    If irregular periods are your main concern, our guide to common causes of irregular periods explains why the clinician considers more than one possibility.

    Frequently asked questions

    Does one ovarian cyst mean I have PCOS?

    No. A cyst alone does not establish the syndrome.

    What is PMOS?

    Polyendocrine metabolic ovarian syndrome is the new name introduced in 2026 for the condition previously called PCOS.

    Are polycystic follicles the same as a large ovarian cyst?

    No. They are different findings and need different interpretation.

    Can PCOS or PMOS be diagnosed without cysts?

    Yes. Clinicians do not need to find separate ovarian cysts to diagnose it.

    Can a scan alone confirm the syndrome?

    No. Diagnosis uses the relevant clinical criteria and assessment, including exclusion of other causes where appropriate.

    Does cyst removal cure the syndrome?

    No. Removing a separate cyst does not automatically treat the broader hormonal and metabolic condition.

    Does either diagnosis prove I cannot become pregnant?

    No. Fertility needs an individual assessment rather than a conclusion from one label.
    PCOS and Ovarian Cysts: Are They the Same Condition?

  • My Anal Fistula Has Stopped Draining: Does That Mean It Has Healed?

    My Anal Fistula Has Stopped Draining: Does That Mean It Has Healed?

    By Shirdi Sai Hospital

    An anal fistula can stop draining without the underlying tract having healed. The skin opening may close temporarily while a connection remains underneath. Some patients then experience another cycle of pain, swelling or discharge.

    Reduced drainage can be encouraging during a planned recovery, but it cannot confirm healing by itself. The meaning depends on whether the fistula is untreated, has a seton or has recently been operated on. Follow-up with the treating surgeon is the safest way to interpret the change.

    If fistula drainage stops and you are unsure what it means, contact the surgical team for advice. However, increasing pain, swelling or fever needs prompt assessment.

    Why can discharge come and go?

    An anal fistula is a tract between the anal canal and nearby skin. It often follows an anal abscess.

    If the external opening remains open, fluid or pus may drain through it. If the opening closes while the tract persists, drainage may stop even though the underlying problem remains.

    Symptoms can therefore fluctuate. A dry interval may be followed by pressure, swelling or renewed discharge.

    That pattern does not mean every patient will develop another abscess. It means that visible dryness is an incomplete measure of healing.

    Tell the surgeon about the whole pattern rather than only how the opening looks on the day of the appointment.

    Is less discharge ever a good sign?

    It can be part of improvement, especially after treatment, but it needs context.

    For example, a healing wound may produce less fluid while pain and swelling settle. In contrast, discharge that stops suddenly as pain and swelling increase can need prompt review.

    The relevant questions are:

    • Is pain improving or becoming worse?
    • Is a new lump or pressure developing?
    • Is there fever or a feeling of illness?
    • Was a seton or another drain deliberately left in place?
    • What did the surgeon expect after the particular procedure?

    Therefore, consider the drainage change alongside those symptoms.

    What if the fistula has not been treated?

    Even without treatment, fistula symptoms can appear to settle for a while. The absence of discharge does not establish that the tract has disappeared.

    Anal fistulas do not usually resolve permanently without appropriate treatment, although the management depends on the cause and anatomy.

    Therefore, keep the surgical appointment even if the opening becomes dry. The clinician can review whether there is persistent disease and what further evaluation is appropriate.

    Do not assume that creams, a short antibiotic course or a dietary change caused a permanent cure simply because symptoms improved afterwards.

    What if you have a seton?

    A surgeon may place a thread-like loop, called a seton, through the fistula tract as part of treatment. Some setons keep the tract draining while the surgeon arranges further care.

    If drainage changes, contact the treating team for advice. The surgeon needs the procedure details and plan to explain a dry opening, loose thread or change in discomfort.

    Do not tighten, cut, pull out or reposition a seton yourself.

    A seton may be one stage of treatment rather than a promise that the fistula has been definitively closed. Ask what the next review is intended to assess.

    What if you recently had fistula surgery?

    Because procedures have different goals, their wounds can also heal differently. An open healing wound cannot be judged in exactly the same way as a tract-closing procedure.

    The surgeon may assess pain, wound appearance, drainage and whether the original symptoms have returned. The follow-up plan should explain what recovery is expected to look like.

    Do not use a photograph of another patient’s wound as the standard for your own healing. Anatomy, procedure and the stage of recovery may differ.

    If you are unsure whether the wound is closing as intended, contact the team. Avoid reopening, probing or putting substances into it at home.

    Does a closed opening prove that no tract remains?

    No. However, the external appearance does not show the entire connection beneath the skin.

    After examining the area and reviewing your symptoms, the clinician decides whether another test would help. MRI or another investigation can be useful for selected complex, persistent or recurrent fistulas.

    Therefore, not every dry opening needs a scan. The decision depends on the clinical question and whether imaging would change management.

    The aim is to identify what is happening, not to order repeated imaging simply because the discharge has varied.

    Which symptoms may suggest another abscess?

    Increasing anal pain, a new tender swelling, pressure, fever or feeling unwell can suggest a collection or another complication.

    Symptoms may become more concerning if the opening stops draining while discomfort and swelling increase.

    Seek prompt medical assessment rather than waiting for the opening to burst. A collection may need drainage, and antibiotics alone are not always sufficient.

    People with diabetes or reduced immunity should be particularly prompt about reporting signs of infection.

    Severe illness, confusion, fainting or rapid deterioration needs emergency care.

    Does recurrent discharge mean treatment definitely failed?

    Not automatically. Some drainage can occur during expected healing, depending on the procedure. Persistent or recurring symptoms can also indicate a fistula that remains or has returned.

    The timing, wound findings and original operation are important. A clinician should distinguish expected recovery from persistence, recurrence or another problem.

    Also bring the procedure summary if another hospital performed the treatment. It may explain whether the fistula was opened, drained, managed with a seton or treated by another method.

    What should you record before review?

    A short symptom record can help the surgeon understand changes between appointments.

    Note when the drainage stopped, whether the area became more painful and whether swelling returned. Record fever or any unplanned medical visits.

    Bring:

    • Previous operation or drainage notes.
    • Relevant MRI or other imaging.
    • Current medicines and antibiotic details.
    • Information about a seton or drain.
    • Any history of Crohn’s disease or other relevant conditions.

    You do not need to repeatedly squeeze or inspect the opening to collect information. Describe what happens naturally.

    What should you avoid doing?

    Do not probe the opening, force drainage or use leftover antibiotics without advice. These actions can injure tissue or delay assessment.

    Follow the wound-care instructions provided for your procedure. Generic advice about packing, massage or cleaning inside a wound may not apply.

    Constipation management may improve bowel comfort, but it does not establish that a persistent tract has healed. Avoid turning a temporary symptom change into a diagnosis.

    If the symptoms are changing, the useful next step is to ask the treating team what the change means.

    When should you see a doctor?

    Arrange review if the opening becomes dry but the diagnosis or follow-up plan remains unclear. Return sooner for increasing pain, swelling, fever or recurring abscess symptoms.

    Our General Surgery department provides a route for assessment of anal discharge and swellings.

    For a planned review at Shirdi Sai Hospital on New BEL Road, contact the hospital with previous reports. Acute infection symptoms should not wait for a routine appointment.

    If you find the terms confusing, our guide to piles, fissure and fistula explains how these conditions differ.

    Frequently asked questions

    Can a fistula stop draining without healing?

    Yes. The skin opening can close temporarily while an underlying tract remains.

    Is less discharge always concerning?

    No. It can occur during recovery. Pain, swelling, fever and the procedure plan help determine its significance.

    Should I cancel review if the opening looks closed?

    No. Confirm the follow-up plan with the treating team.

    Should I reopen the opening to let it drain?

    No. Do not probe or force it open yourself.

    Can antibiotics permanently close every fistula?

    No. Antibiotics are not a universal treatment for an established fistula tract.

    Is an MRI always needed?

    No. The clinician requests imaging if it can clarify the tract or change treatment.

    What if drainage stops and swelling increases?

    Seek prompt assessment, particularly if pain, fever or feeling unwell develops.

  • Can a Hernia Belt Cure a Hernia?

    Can a Hernia Belt Cure a Hernia?

    By Shirdi Sai Hospital

    A hernia belt cannot close the defect causing an adult groin hernia. It may provide temporary support or reduce discomfort for selected patients, but a flatter-looking bulge while wearing it does not mean that the hernia has healed.

    The decision about a belt should follow assessment. For example, a clinician may suggest one while discussing a longer-term plan. However, others need a different approach. Buying a stronger or tighter belt is not a substitute for understanding the hernia and its symptoms.

    If you rely on a hernia belt for comfort, arrange a surgical assessment so you understand its limits and your treatment options.

    Why can the bulge look smaller without being cured?

    An inguinal hernia involves tissue pushing through a weak area in the groin. For example, the bulge may vary with position, coughing or activity.

    However, external support can change how noticeable the bulge feels or looks. It does not, however, repair the opening in the tissue.

    Therefore, the swelling can return after you remove the belt. That change is not proof that the patient wore it incorrectly. It reflects the difference between supporting a hernia and repairing it.

    The same distinction applies when a bulge becomes smaller after lying down. A change in appearance is not a test of permanent healing.

    What can a belt or truss sometimes do?

    For example, a suitable device may temporarily ease discomfort from a hernia that reduces when you lie down. A clinician may discuss it while planning surgery or if the risks favour another approach.

    Before using one, get advice about whether it suits the hernia and how it should fit. Not every groin swelling is a hernia, and not every hernia is suitable for the same support.

    Therefore, a belt should have a clear purpose. Ask whether it is intended to improve comfort, help with a particular activity or support a temporary management plan.

    It should not come with a promise that prolonged use will make the defect disappear.

    Does feeling better mean the hernia is safe?

    Although less discomfort helps, it does not prove that the defect has healed or that complications are impossible.

    However, symptoms can change. A previously manageable hernia may become more painful, larger or difficult to reduce.

    Also, a belt should not encourage you to continue an activity that repeatedly causes significant pain. The response should be reassessment, not simply increasing the belt pressure.

    Tell the surgeon whether the device helps, causes skin irritation or allows the bulge to appear around it. As a result, those details may affect advice.

    Why not choose the tightest available belt?

    However, a very tight device is not automatically more effective. An unsuitable fit can cause discomfort, pressure or skin problems and may fail to support the correct area.

    Do not use pain as a sign that the belt is “working.” A device that makes the lump more painful or causes new symptoms needs review.

    A new painful or stuck swelling should not be forced into place to make a belt fit. Seek medical assessment.

    Online fitting instructions cannot establish that a particular hernia is appropriate for a truss. The first question is clinical suitability, not which product has the strongest compression.

    Can exercise or a belt replace repair?

    Similarly, exercises do not reliably close an established adult groin hernia. Activity advice should focus on what is safe and tolerable in the individual situation.

    A belt may help selected symptoms, but it does not turn an unsuitable activity into a safe one for every patient.

    That does not mean everyone with a hernia must stop all movement. Ask about walking, work, exercise and lifting in relation to your symptoms and treatment plan.

    Avoid extreme online claims in either direction: “all exercise will cause an emergency” and “stronger abdominal muscles will cure the hernia” are not useful rules for an individual patient.

    Does every hernia need an immediate operation?

    No. Some patients may be suitable for a period of observation after assessment. In contrast, a surgeon may recommend repair because of symptoms, progression or clinical risk.

    Observation and a belt are not the same thing. A monitored plan can include advice about symptoms, follow-up and what would change the recommendation.

    Even if pain is mild, a clinician must assess the lump before recommending observation. Age, sex, hernia type, examination and other health factors matter.

    Our guide to hernia surgery in New BEL Road explains the assessment and treatment pathway.

    What if you already had a repair?

    If a bulge appears after surgery, arrange a review rather than simply reusing an old belt.

    For example, the cause may be recurrence or another problem after surgery. The surgeon needs to understand the earlier operation and current findings.

    Bring the previous operation note if available. A belt cannot tell us whether the repair has recurred or which treatment would be appropriate.

    If you are considering repeat repair, the earlier operation can influence the next decision. A temporary improvement with support does not remove the need for that assessment.

    When should you see a doctor?

    Arrange assessment for a new groin lump, increasing discomfort, a bulge affecting work or daily activity, or a change in a known hernia.

    If a clinician has recommended a belt, ask when the hernia should be reviewed and what to do if the device stops helping.

    Seek urgent care for a suddenly painful, firm or stuck swelling, especially with vomiting, abdominal swelling, inability to pass stool or gas, fever or skin changes.

    Do not keep tightening the belt, forcefully push the lump back or wait for an online response during those symptoms.

    What should you ask at a consultation?

    A useful consultation should clarify the diagnosis and the purpose of any support device.

    Ask:

    • Is this definitely an inguinal hernia?
    • Is observation reasonable in my situation?
    • Would a belt help, and who should fit it?
    • Which activities need modification?
    • What symptoms should change the plan?
    • If the surgeon recommends repair, why and how urgently?

    Explain your work duties and any relevant health conditions.

    Choosing the next step

    A belt can be a comfort measure for selected patients. It is not a cure, and it should not delay assessment of changing symptoms.

    For a planned surgical consultation, you can contact Shirdi Sai Hospital on New BEL Road. Bring any previous reports and describe whether the swelling is new, longstanding or present after repair.

    Before using support to continue lifting, read about hernia symptoms during exercise. A belt does not remove the need to adjust painful activities.

    Frequently asked questions

    Can a hernia belt permanently cure a hernia?

    No. It does not close the underlying tissue defect.

    Why does the lump disappear while I wear it?

    External support can reduce the bulge’s prominence without repairing the weak area.

    Can I wear a tighter belt to avoid surgery?

    Do not increase pressure as a substitute for assessment. Suitability and fit need advice.

    Does everyone need a hernia belt?

    No. Some patients may use one selectively, while others need a different plan.

    Can I lift heavy weights if I wear one?

    A belt does not automatically make lifting safe. Discuss activity in relation to symptoms and treatment.

    Does a painless hernia need no follow-up?

    Not necessarily. A clinician should first assess the hernia and explain the review plan.

    What if the lump becomes painful and stuck?

    Seek urgent medical assessment. Do not force it back or rely on the belt.

  • Burning Sensation While Urinating: When It’s Not Just a UTI

    Burning Sensation While Urinating: When It’s Not Just a UTI

    A burning sensation while passing urine is one of the most uncomfortable symptoms people experience. The first thought for most patients is a urinary tract infection (UTI), and many start antibiotics on their own. Sometimes the burning reduces. Sometimes it does not. In many cases, the symptom keeps returning.

    This leads to confusion.

    The truth is simple. Burning while urinating is not always caused by a UTI. Several other conditions can produce the same sensation, and treating everything as an infection may delay the right care.

    This blog explains the common causes of burning urination, when it is a UTI, and when it is something else that needs medical attention.

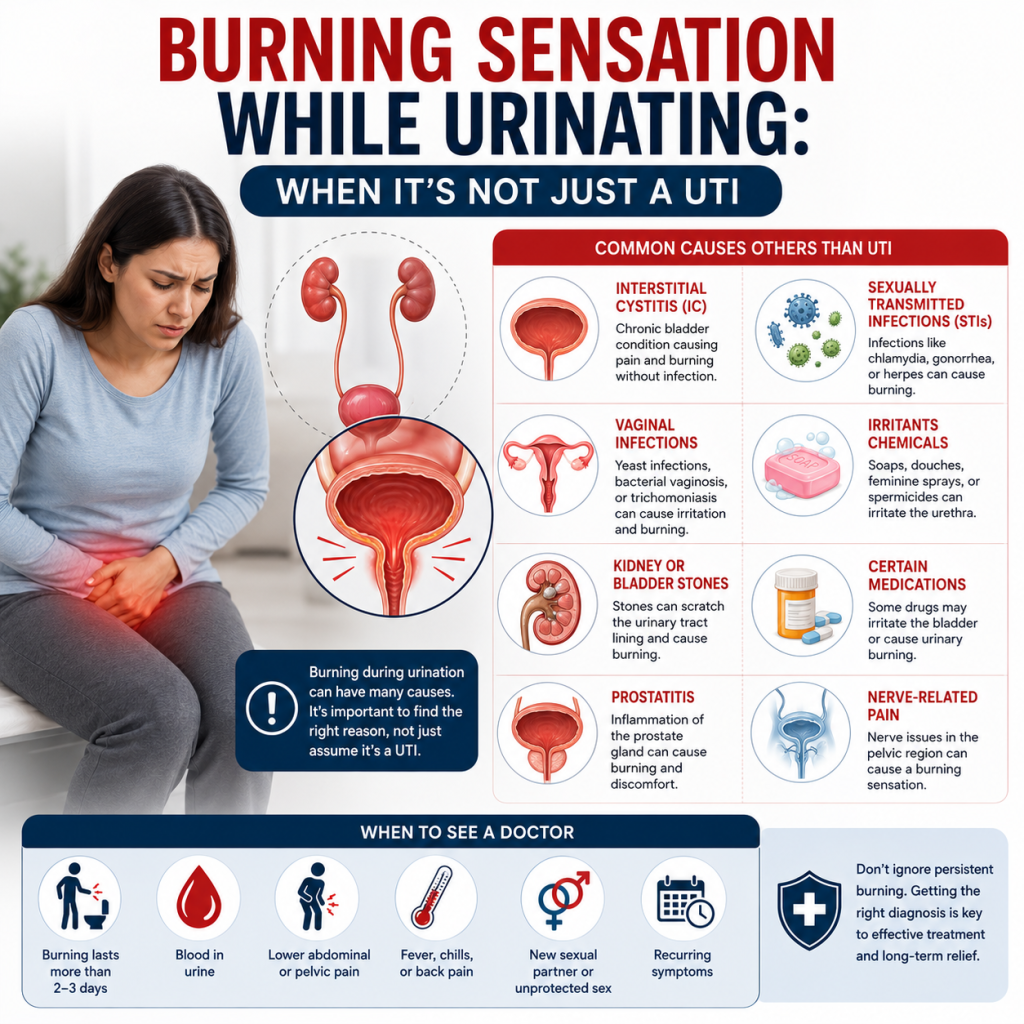
    Medical infographic explaining that a burning sensation while urinating is not always caused by a urinary tract infection (UTI), highlighting alternative causes such as sexually transmitted infections, vaginal infections, kidney stones, interstitial cystitis, medications, irritants, and warning signs that require medical evaluation.

    What causes a burning sensation while urinating?

    Burning during urination happens when the lining of the urinary tract becomes irritated or inflamed. This irritation may be due to infection, inflammation, stones, or even external factors.

    Because multiple conditions affect the same urinary passage, symptoms often overlap, making self-diagnosis unreliable.


    When burning urination is caused by a UTI

    UTI is one of the most common causes, especially in women.

    Typical signs include:

    • Burning while passing urine
    • Frequent urge to urinate
    • Passing small amounts of urine
    • Cloudy or foul-smelling urine
    • Lower abdominal discomfort

    In such cases, antibiotics prescribed after urine testing usually resolve symptoms within a few days.


    When burning urination is NOT just a UTI

    Many patients are surprised to learn that burning can occur even when urine tests are normal.

    Dehydration

    Low water intake can concentrate urine, making it more acidic. This concentrated urine can cause burning even without infection.

    Urinary stones

    Small stones or crystals can irritate the urinary tract, causing burning, pain, or blood in urine.

    Prostate-related issues (in men)

    Prostate inflammation or enlargement can lead to burning, weak urine flow, or difficulty emptying the bladder.

    Vaginal or genital infections

    In women, vaginal infections or local irritation can cause burning that feels like urinary pain, even when the bladder is normal.

    Sexually transmitted infections

    Some infections affect the urethra and cause burning without typical UTI findings. These need specific testing and treatment.

    Chemical or hygiene-related irritation

    Harsh soaps, intimate washes, or spermicides can irritate sensitive areas and cause burning sensations.


    Common medicines used for burning urination

    Treatment depends entirely on the cause.

    • Antibiotics are used only when infection is confirmed
    • Urinary alkalizers may be prescribed to reduce urine acidity
    • Pain-relief medicines may ease discomfort temporarily
    • Targeted treatment is required for stones, prostate issues, or genital infections

    Using antibiotics repeatedly without confirmation may reduce symptoms briefly but does not solve the underlying issue.


    Warning signs you should not ignore

    Consult a doctor if you notice:

    • Burning that persists for more than two to three days
    • Fever or chills
    • Blood in urine
    • Severe lower abdominal or back pain
    • Burning associated with discharge or itching
    • Recurrent episodes despite medicines

    These signs usually indicate a cause beyond simple irritation.


    How doctors evaluate burning urination at Shirdi Sai Hospital

    At Shirdi Sai Hospital, consultants focus on identifying the exact reason behind the symptom. Evaluation may include:

    • Urine routine and culture tests
    • Ultrasound if stones or obstruction are suspected
    • Blood tests when needed
    • Examination for prostate or genital causes
    • Review of hygiene and lifestyle factors

    This step-by-step approach avoids unnecessary medicines and ensures accurate treatment.


    Frequently asked questions

    Is burning urination always due to infection?
    No. Dehydration, stones, irritation, or prostate issues can also cause burning.

    Can drinking more water reduce burning?
    Yes, in mild cases caused by concentrated urine, hydration helps.

    Is it safe to take antibiotics without testing?
    Repeated antibiotic use without tests is not recommended.

    Why does burning return after treatment?
    Because the underlying cause may not have been addressed.

    When should I see a doctor?
    If burning is persistent, severe, or keeps recurring.


    When to consult a doctor

    If burning while urinating keeps coming back or does not improve with basic measures, early evaluation can prevent complications and repeated discomfort.

    📞 Call Shirdi Sai Hospital, Bangalore
    OPD consultation starts from ₹500
    Consultants will guide you with the right diagnosis and treatment.

  • Hormonal Tablets for Irregular Periods: What Patients Should Know

    Hormonal Tablets for Irregular Periods: What Patients Should Know

    Irregular periods are one of the most common reasons women look for hormonal tablets. A missed cycle, delayed periods, or frequent spotting can be stressful, especially when it starts affecting daily routine or future pregnancy plans. Many women are prescribed hormonal tablets and notice that periods become regular while the medicine is taken. Once the tablets stop, the cycle becomes irregular again.

    This leads to confusion and concern.

    Hormonal tablets can be useful, but they are not a one-size-fits-all solution. Understanding why periods are irregular is more important than simply restarting tablets each time.

    This blog explains what hormonal tablets do, when they are prescribed, and when irregular periods need proper medical evaluation.

    Medical infographic explaining hormonal tablets for irregular periods, featuring the female reproductive system, common causes of irregular menstrual cycles, types of hormonal medications, potential side effects, precautions, and guidance for safe use.

    What are irregular periods?

    A menstrual cycle is considered irregular when:

    • Periods come too early or too late
    • Cycles vary widely each month
    • Bleeding lasts too long or is very light
    • Periods are missed frequently

    Occasional variation can be normal. Repeated irregularity usually points to an underlying imbalance.


    Common reasons for irregular periods

    Irregular cycles can occur for many reasons, including:

    Because the causes vary, treatment also differs from person to person.


    Hormonal tablets commonly prescribed for irregular periods

    Doctors prescribe hormonal tablets after understanding the cycle pattern and medical history.

    Progesterone-based tablets

    These are commonly used to trigger periods when cycles are delayed. They help shed the uterine lining and bring a withdrawal bleed.

    Combined hormonal tablets

    These tablets contain both estrogen and progesterone. They help regulate cycles and reduce heavy or irregular bleeding in selected patients.

    Hormonal regulation in specific conditions

    In conditions like PCOS, hormonal tablets may be part of a broader treatment plan that also includes lifestyle changes.

    Hormonal tablets are prescribed for regulation, not as a permanent fix without evaluation.


    When hormonal tablets help

    Hormonal tablets are useful when:

    • Irregular periods are due to temporary hormonal imbalance
    • Cycles need short-term regulation
    • Heavy or unpredictable bleeding needs control
    • Tablets are used under medical supervision

    In these cases, periods become predictable while treatment continues.


    Why periods become irregular again after stopping tablets

    This is a common concern.

    Periods may become irregular again if:

    • The underlying cause was not addressed
    • Lifestyle factors like stress or weight remain unchanged
    • Conditions like PCOS or thyroid disorders are present
    • Hormones were used only to induce bleeding

    Tablets regulate the cycle temporarily. They do not correct the root cause on their own.


    Warning signs you should not ignore

    Consult a doctor if you notice:

    • Periods stopping for several months
    • Very heavy or prolonged bleeding
    • Irregular periods with acne or excess hair growth
    • Sudden changes in cycle pattern
    • Irregular periods while planning pregnancy

    These signs usually need evaluation rather than repeated hormonal tablets.


    How doctors evaluate irregular periods at Shirdi Sai Hospital

    At Shirdi Sai Hospital, consultants focus on identifying the reason behind cycle irregularity. Evaluation may include:

    • Detailed menstrual and lifestyle history
    • Hormonal blood tests if required
    • Thyroid assessment
    • Ultrasound to check ovaries and uterus
    • Guidance on safe use of medicines

    The goal is to restore natural cycle balance whenever possible, not just induce periods.


    Frequently asked questions

    Are hormonal tablets safe for long-term use?
    They may be safe in selected cases under supervision, but long-term use should always be reviewed.

    Do hormonal tablets affect future fertility?
    When used appropriately, they do not harm fertility. Underlying conditions matter more.

    Is it okay to take hormonal tablets every time periods are delayed?
    Repeated use without evaluation is not recommended.

    Can lifestyle changes improve irregular periods?
    Yes. Weight management, stress reduction, and sleep can significantly help.

    When should I see a doctor for irregular periods?
    If irregularity persists, worsens, or affects pregnancy planning.


    When to consult a doctor

    If periods remain irregular or you depend on hormonal tablets repeatedly, early evaluation can prevent long-term hormonal and reproductive issues.

    📞 Call Shirdi Sai Hospital, Bangalore
    OPD consultation starts from ₹500
    Consultants will guide you with safe and personalised care.

  • Period Pain Medicines: What’s Safe and What Needs Medical Advice

    Period Pain Medicines: What’s Safe and What Needs Medical Advice

    Period pain is common, but it is also one of the most misunderstood problems. Many women push through cramps with painkillers every month, assuming this is normal and something they must tolerate. For some, tablets work well and life continues as usual. For others, pain keeps increasing, tablets stop helping, or new symptoms appear.

    The difference lies in why the pain is happening.

    This blog explains which medicines are commonly used for period pain, when they are considered safe, and when pain during periods needs medical attention rather than repeated tablets.

    Medical infographic explaining period pain medicines, comparing safe treatment options with medications that require medical supervision, along with self-care measures, safety tips, and warning signs that need a doctor's evaluation.

    Why period pain happens

    Pain during periods, also called dysmenorrhea, happens due to strong uterine contractions. These contractions help shed the uterine lining, but in some women they become intense and painful.

    Common reasons include:

    • Hormonal changes during the menstrual cycle
    • Increased prostaglandins causing strong contractions
    • Stress and poor sleep
    • Underlying conditions like fibroids or endometriosis
    • Irregular cycles or hormonal imbalance

    Mild pain on the first day can be normal. Severe or worsening pain is not something to ignore.


    Common medicines used for period pain

    Doctors usually recommend medicines based on pain severity, cycle regularity, and overall health.

    Painkillers and anti-inflammatory medicines

    Medicines such as paracetamol, mefenamic acid, and other anti-inflammatory tablets are commonly used. They reduce pain and inflammation during periods and work well for mild to moderate cramps.

    Antispasmodic medicines

    These medicines help relax uterine muscles and reduce cramping. They are often used when pain feels tight or spasmodic.

    Hormonal medicines

    In some cases, doctors prescribe hormonal tablets to regulate cycles and reduce pain. These are used only after proper evaluation and are not meant for casual or short-term use.

    All period pain medicines should be taken under medical guidance, especially if needed every month.


    When period pain medicines usually work

    Medicines are often effective when:

    • Pain is mild to moderate
    • Cycles are regular
    • Pain improves within a day or two
    • No other symptoms are present

    In such cases, tablets help control discomfort without affecting daily routine.


    When tablets are not enough

    This is where many women delay care.

    Period pain needs medical attention if:

    • Pain is severe and affects work or daily activities
    • Tablets are needed every month without relief
    • Pain worsens over time
    • Periods are very heavy or prolonged
    • Pain occurs outside the menstrual period

    Repeated painkillers may reduce pain temporarily, but they do not treat underlying problems.


    Warning signs you should not ignore

    Consult a doctor if you notice:

    • Period pain that suddenly becomes severe
    • Pain not responding to usual medicines
    • Heavy bleeding or large clots
    • Irregular or missed periods
    • Pain during intercourse
    • Fatigue or dizziness during periods

    These signs often point to conditions that need evaluation.


    How doctors evaluate period pain at Shirdi Sai Hospital

    Consultants at Shirdi Sai Hospital focus on understanding the cause of pain. Evaluation may include:

    • Detailed menstrual history
    • Hormonal assessment if required
    • Ultrasound to check uterus and ovaries
    • Guidance on safe medication use
    • Long-term management planning

    The aim is to reduce pain safely while protecting reproductive health.


    Frequently asked questions

    Is it safe to take painkillers every month for periods?
    Occasional use may be safe, but regular monthly use should be discussed with a doctor.

    Do hormonal tablets permanently stop period pain?
    They can reduce pain in some women, but they are prescribed only after evaluation.

    Is period pain normal after marriage or childbirth?
    Pain patterns can change, but severe pain is not normal at any stage.

    Can home remedies replace medicines?
    They may provide comfort, but they cannot treat medical causes of pain.

    When should I see a doctor for period pain?
    If pain affects daily life or keeps worsening over time.


    When to consult a doctor

    If period pain is disrupting your routine or tablets no longer help, it is better to seek medical advice early.

    📞 Call Shirdi Sai Hospital, Bangalore
    OPD consultation starts from ₹500
    Consultants will guide you with safe and appropriate care.

  • Painkillers for Knee Pain: When Relief Is Temporary

    Painkillers for Knee Pain: When Relief Is Temporary

    Knee pain is one of the most common reasons people reach for painkillers. After a long day at work, climbing stairs, or starting a new walking routine, the knee starts hurting. One tablet reduces the pain, and life goes on. A few days later, the pain returns. Another tablet follows.

    This cycle is extremely common in Bangalore. Painkillers do help, but they are not designed to fix what is causing knee pain. Understanding this early can prevent long-term joint problems.

    This blog explains which painkillers are commonly used for knee pain, when they are useful, and when relief from tablets is only temporary.

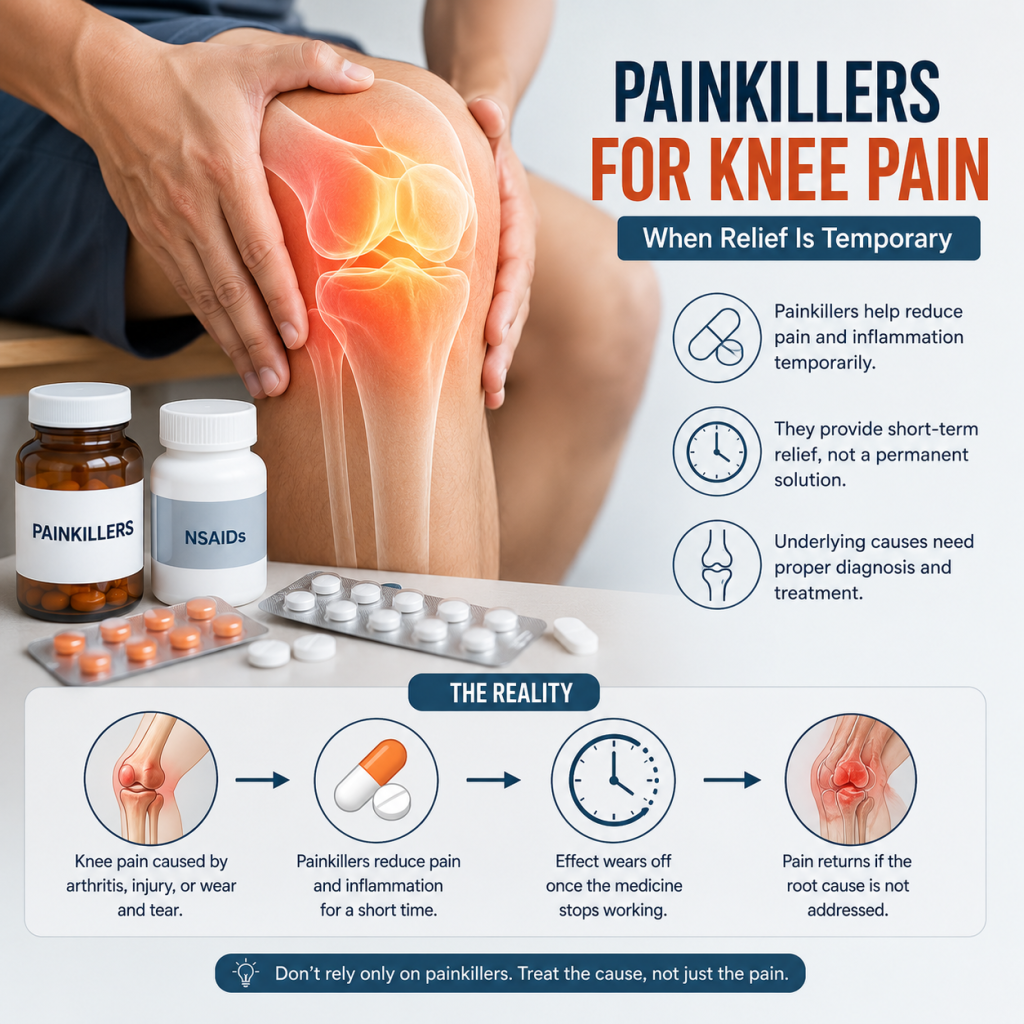
    Illustration of a painful knee joint with an anatomical overlay, painkiller tablets, and a visual timeline explaining that painkillers provide temporary relief for knee pain but do not treat the underlying cause.

    Why knee pain has become so common today

    Knee pain is no longer limited to older adults. Doctors now see it in people as young as their thirties.

    Common reasons include:

    • Long hours of sitting at desks
    • Sudden increase in walking, jogging, or gym workouts
    • Weight gain putting extra load on the knee
    • Previous sports or accident-related injuries
    • Early wear and tear of joint cartilage

    Knee pain is often blamed on age, but in many cases, lifestyle and movement patterns play a bigger role.


    Common painkillers used for knee pain

    Painkillers are usually the first line of relief. Some commonly used medicines include:

    Paracetamol

    Paracetamol is often used for mild knee pain. It helps reduce pain but has very little effect on inflammation.

    NSAIDs for knee pain

    Medicines such as diclofenac and aceclofenac belong to a group called non-steroidal anti-inflammatory drugs. They reduce both pain and inflammation and are commonly prescribed for knee problems.

    Combination painkillers

    Some tablets combine pain-relief and anti-inflammatory components. These may provide stronger short-term relief but do not address the underlying joint issue.

    Pain relief gels and sprays

    Topical gels can temporarily reduce discomfort, especially after activity. However, their effect is usually short-lived.

    These medicines reduce pain signals and inflammation, not joint damage or structural problems.


    When painkillers genuinely help

    Painkillers can be useful when:

    • Knee pain is due to a recent strain or overuse
    • There is mild inflammation
    • Pain occurs during an acute flare-up
    • They are used along with rest and physiotherapy

    In these situations, tablets provide comfort while the knee heals. Relief is expected to be temporary, not permanent.


    When painkillers stop working

    This is where many people get stuck.

    Painkillers may stop giving lasting relief when:

    • There is cartilage wear or early arthritis
    • Ligaments or meniscus are injured
    • Knee alignment is altered
    • Muscle weakness is not corrected
    • Pain is repeatedly masked without evaluation

    A common warning sign is when pain returns faster each time, even after taking tablets.


    Risks of long-term painkiller use

    Using painkillers occasionally is generally safe. Long-term or frequent use without medical supervision can lead to problems such as:

    • Stomach irritation or ulcers
    • Kidney strain
    • Increase in blood pressure
    • Reduced effectiveness of medicines over time

    This is why knee pain should not be managed with tablets alone for months.


    Warning signs you should not ignore

    Consult an orthopaedic doctor if you notice:

    • Knee pain lasting more than two to three weeks
    • Swelling or stiffness around the joint
    • Difficulty climbing stairs or getting up from a chair
    • Knee giving way while walking
    • Pain present even at rest or during the night

    These signs usually indicate that the knee needs evaluation beyond pain relief.


    How orthopaedic doctors evaluate knee pain

    At Shirdi Sai Hospital, knee pain is assessed step by step. Evaluation may include:

    • Detailed clinical examination
    • X-ray or MRI when required
    • Assessment of joint alignment
    • Muscle strength and movement analysis
    • Treatment planning beyond painkillers

    The focus is on protecting the joint and improving function, not just reducing pain for a few hours.


    Frequently asked questions

    Is it safe to take painkillers daily for knee pain?
    Daily use without medical advice is not recommended, especially for long periods.

    Why does knee pain return after taking tablets?
    Because painkillers do not correct cartilage damage, alignment issues, or muscle weakness.

    Can physiotherapy reduce the need for painkillers?
    Yes. Strengthening and movement correction often reduce pain significantly.

    Are injections better than tablets for knee pain?
    Injections are used in selected cases after proper evaluation. They are not the first step for everyone.

    When should I see an orthopaedic doctor?
    If pain keeps returning, worsens, or affects daily activities.


    When to consult a doctor

    If knee pain is limiting your movement or returning repeatedly despite painkillers, it is better to get the joint checked early.

    📞 Call Shirdi Sai Hospital, Bangalore
    OPD consultation starts from ₹500
    Consultants will guide you with the right evaluation and treatment plan.

  • Tablets for Frequent Urination at Night: Do They Really Work?

    Tablets for Frequent Urination at Night: Do They Really Work?

    Waking up two or three times every night to pass urine can slowly drain your energy. Sleep breaks, mornings feel heavy, and the day starts tired. Many people in Bangalore assume this is just age or stress and look for a tablet that will “settle the bladder.” Tablets can help in some situations, but night-time urination often has more than one cause. That is why medicines work for some people and not for others.

    This guide explains which tablets are commonly prescribed, when they help, and when it is better to get checked instead of continuing medicines on your own.

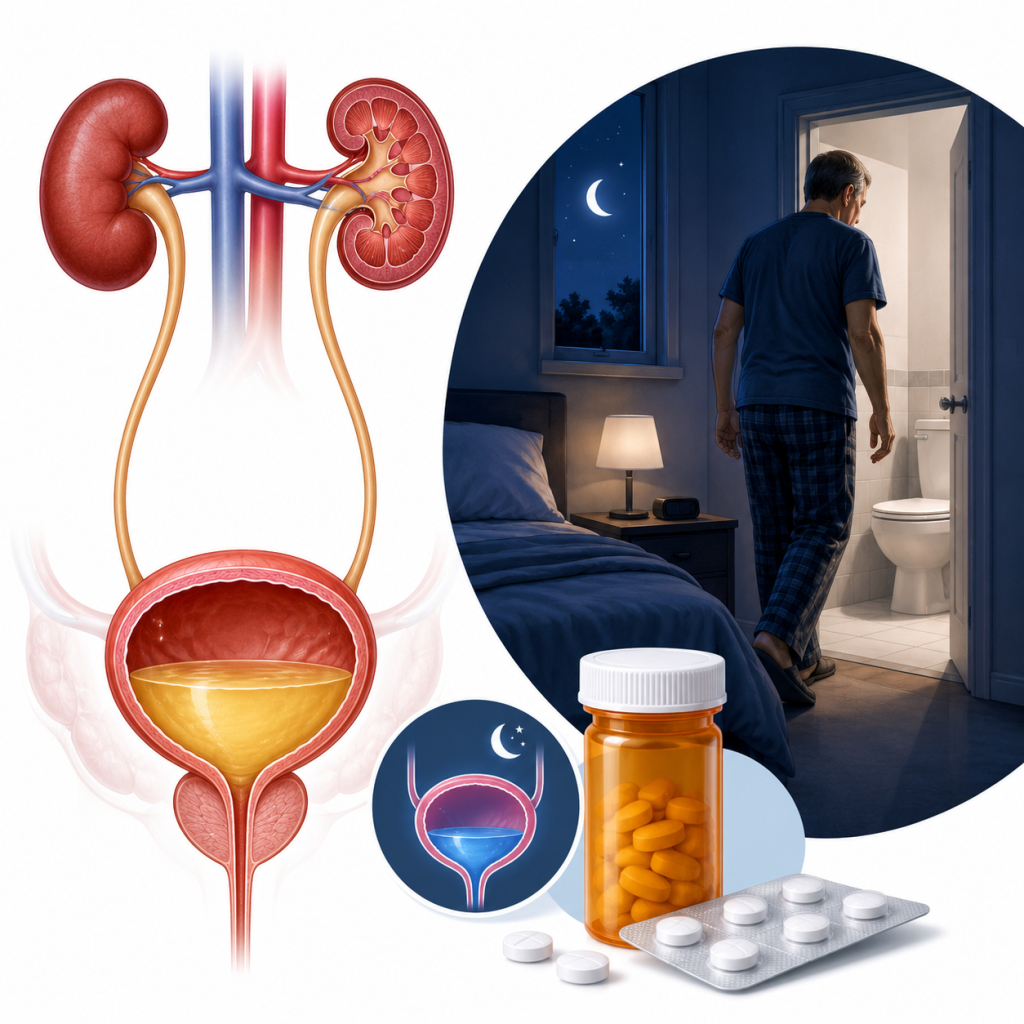
    Medical illustration showing the urinary system, a man waking at night to use the bathroom, and tablets representing treatment for frequent nighttime urination.

    What is frequent urination at night?

    Passing urine more than once at night is called nocturia. One visit occasionally can be normal, especially if you drink a lot of fluids late in the evening. Waking up repeatedly, night after night, is not normal and usually points to an underlying issue.


    Common reasons people pass urine frequently at night

    Night-time urination is a symptom, not a disease. Common causes include:

    • Enlarged prostate in men above 40
    • Overactive bladder, where the bladder contracts too often
    • Diabetes or poorly controlled blood sugar
    • Urinary tract infection, especially if burning is present
    • Excess evening fluids, tea, coffee, or alcohol
    • Certain blood pressure medicines that increase urine output

    Many patients have more than one reason at the same time, which is why a single tablet may not fully solve the problem.


    Common tablets prescribed for frequent urination at night

    Doctors choose medicines only after understanding the cause. Some commonly used tablets include:

    Medicines for overactive bladder

    Antimuscarinic medicines such as oxybutynin and tolterodine help relax the bladder muscle. They reduce urgency and frequent urges, including at night. These medicines work best when overactive bladder is the main issue.

    Medicines for prostate-related symptoms

    In men with prostate enlargement, alpha blockers like tamsulosin improve urine flow and reduce night-time frequency. These medicines address blockage, not bladder weakness.

    When antibiotics are used

    If frequent urination is due to a urinary infection, antibiotics are prescribed based on urine test results. Taking antibiotics without confirmation may temporarily reduce symptoms but not clear the infection.

    What medicines cannot fix

    Sleeping pills and painkillers do not treat the cause of night urination. They may improve sleep for a short time while the underlying problem continues.

    These medicines are prescribed only after evaluation and are not meant for self-use.


    When tablets actually help

    Medicines usually work well when:

    • The cause is correctly identified
    • Only one main issue is present
    • Tablets are taken regularly as advised
    • Lifestyle adjustments are followed alongside treatment

    Improvement is usually gradual over a few weeks, not overnight.


    Why tablets may not solve the problem

    This is where many people get stuck.

    Tablets may not give lasting relief if:

    • The diagnosis is incomplete
    • Diabetes or blood pressure is uncontrolled
    • Prostate enlargement is significant
    • Kidney or heart-related fluid issues are present
    • Medicines are taken irregularly or stopped early

    In such cases, medicines may reduce night trips for a while, but the problem returns.


    Warning signs you should not ignore

    Seek medical advice if you notice:

    • Sudden increase in night-time urination
    • Burning or pain while passing urine
    • Blood in urine
    • Weak or interrupted urine flow
    • Swelling of legs or breathlessness during the day

    These signs need evaluation rather than repeated tablet changes.


    How doctors evaluate frequent urination at night

    At Shirdi Sai Hospital, consultants look beyond symptoms and focus on the cause. Evaluation may include:

    • Urine routine and culture tests
    • Blood sugar assessment
    • Ultrasound of the abdomen or prostate
    • Review of current medications
    • Lifestyle and fluid-intake assessment

    This approach helps avoid long-term medicine dependence and repeated symptoms.


    Frequently asked questions

    Is frequent urination at night normal with age?
    Age increases risk, but repeated night-time urination should still be evaluated.

    Do prostate tablets need to be taken lifelong?
    Not always. Duration depends on symptoms, prostate size, and response.

    Can diabetes cause night-time urination?
    Yes. High blood sugar leads to excess urine production, especially at night.

    Are these tablets habit-forming?
    Most are not habit-forming, but they should be taken only under guidance.

    When should I see a doctor?
    If night urination affects sleep, recurs often, or is associated with pain or burning.


    When to consult a doctor

    If night-time urination is disturbing your sleep or tablets are not giving consistent relief, it is better to get clarity on the cause.

    📞 Call Shirdi Sai Hospital, Bangalore
    OPD consultation starts from ₹500
    Consultants will help identify the reason and guide safe treatment.